
Clinical Practice Guidelines
ANN M. LUCADO, PT, PhD, CHT • JOSEPH M. DAY, PT, PhD, OCS • JOSHUA I. VINCENT, PT, PhD
JOY C. MACDERMID, PT, PhD, CHT • JANE FEDORCZYK, PT, PhD, CHT
RUBY GREWAL, MD • ROBROY L. MARTIN, PT, PhD
Lateral Elbow Pain and Muscle
Function Impairments
Clinical Practice Guidelines Linked to the International Classification
of Functioning, Disability and Health from the Academy of Hand and
Upper Extremity Physical Therapy and the Academy of Orthopaedic
Physical Therapy of the American Physical Therapy Association
J Orthop Sports Phys Ther. 2022;52(12):CPG1-CPG111. doi:10.2519/jospt.2022.0302
For author, coordinator, contributor, and reviewer aliations, see end of text. ©2022 Academy of Orthopaedic Physical Therapy, Academy of Hand and Upper Extremity
Physical Therapy, American Physical Therapy Association (APTA), Inc, and JOSPT
®
, Inc. The Academy of Orthopaedic Physical Therapy, Academy of Hand and Upper
Extremity Physical Therapy, APTA, Inc, and JOSPT
®
, Inc consent to reproducing and distributing this guideline for educational purposes. Address correspondence to Clinical
Practice Guidelines Managing Editor, Academy of Orthopaedic Physical Therapy, APTA, Inc, 2920 East Avenue South, Suite 200, La Crosse, WI 54601. E-mail: [email protected]
SUMMARY OF RECOMMENDATIONS ................................CPG2
INTRODUCTION .................................................................CPG4
METHODS ..........................................................................CPG5
CLINICAL PRACTICE GUIDELINES:
Impairment/Function-Based Diagnosis ............................ CPG8
Pathoanatomical Features .................................................. CPG8
Risk Factors ......................................................................... CPG9
Clinical Course ................................................................... CPG10
Prognosis ............................................................................ CPG11
Diagnosis/Classification .................................................... CPG12
Examination ........................................................................ CPG15
Interventions ...................................................................... CPG25
DECISION TREE ...............................................................CPG43
AUTHOR/REVIEWER AFFILIATIONS AND CONTACTS ... CPG45
REFERENCES ...................................................................CPG46
APPENDICES ................................................................... CPG53
REVIEWERS: John DeWitt, PT, DPT, AT • Steve Paulseth, PT, DPT, SCS, ATC • James A. Dauber, DPT, DSc
Mike Szekeres, PhD, OT Reg (Ontario), CHT • Paul F. Beattie, PhD, PT, OCS, FAPTA, NREMT
Journal of Orthopaedic & Sports Physical Therapy®
Downloaded from www.jospt.org at on January 15, 2023. For personal use only. No other uses without permission.
Copyright © 2022 Journal of Orthopaedic & Sports Physical Therapy®. All rights reserved.
cpg2 | december 2022 | volume 52 | number 12 | journal of orthopaedic & sports physical therapy
Lateral Elbow Pain and Muscle Function Impairments: Clinical Practice GuidelinesLateral Elbow Pain and Muscle Function Impairments: Clinical Practice Guidelines
Summary of Recommendations*
OUTCOME, ACTIVITY LIMITATIONS,
SELF-REPORT MEASURES
A
Clinicians should use the diagnosis-specific Patient-Rated
Tennis Elbow Evaluation (PRTEE) to assess pain/irritability
and function and/or the region-specific Disabilities of the Arm,
Shoulder and Hand (DASH) to assess upper extremity function at
baseline and at least one other follow-up point that includes dis-
charge for individuals with lateral elbow tendinopathy (LET).
A
Clinicians should use the Patient-Specific Functional Scale
(PSFS) for patients with high-demand activities and/or should
administer a scale that assesses activity-specific disability (eg, DASH
work or sports/performing arts module) at baseline and at least one
other follow-up point that includes discharge for individuals with LET.
PHYSICAL IMPAIRMENT MEASURES
B
Clinicians should include the physical impairment mea-
sures of elbow and wrist range of motion, pressure pain
threshold, pain-free grip strength, and maximum grip strength at
baseline and at least one other follow-up point that includes dis-
charge for individuals with LET.
INTERVENTIONS: THERAPEUTIC EXERCISE
B
Clinicians should use isometric, concentric, and/or eccen-
tric therapeutic resisted exercises of the wrist extensors in
the treatment of individuals with subacute or chronic LET.
F
Clinicians may use a phased approach to reintroduce stress,
increase strength, improve endurance, and restore optimal
motor control in individuals who have LET symptoms with high-de-
mand occupations, hobbies, performing arts, or athletic interests.
MULTIMODAL INTERVENTIONS: INCLUDING
THERAPEUTIC EXERCISE
B
Clinicians should use therapeutic resisted wrist extension
strengthening exercises in combination with other thera-
peutic interventions, including manual therapy, in the treatment
of patients with subacute or chronic LET.
C
Clinicians may include shoulder and scapular stabilizer
muscle training exercises, when impairments are identi-
fied, in conjunction with other forms of wrist extensor strengthen-
ing exercise in individuals with LET.
INTERVENTIONS: MANUAL THERAPY JOINT
MOBILIZATIONS/MANIPULATIONS
B
Clinicians should use local elbow joint manipulation or
mobilization techniques to reduce pain and increase pain-
free grip strength in individuals with LET, as a stand-alone or ad-
junctive treatment in improving short-term outcomes for those
who can tolerate the specific technique.
C
Clinicians may use manipulation or mobilization techniques
directed at the cervical spine, thoracic spine, and/or wrist as
an adjunct to local treatment for short-term pain relief in individuals
with LET when impairments in those regions are identified.
INTERVENTIONS: MANUAL THERAPY
SOFT TISSUE MOBILIZATION
C
Clinicians may use soft tissue mobilizations, including
manual release therapy, to improve pain and function in
individuals with chronic LET.
C
Clinicians may use instrument-assisted soft tissue mobili-
zation combined with exercise to improve pain and func-
tion in those with chronic LET.
D
Based on conflicting evidence, a recommendation cannot be
made regarding the use of deep transverse tendon cross-fric-
tion massage to alleviate symptoms in individuals with LET.
INTERVENTIONS: DRY NEEDLING
B
Clinicians should use either tendon or trigger point dry
needling for the treatment of pain and functional deficits
associated with LET.
INTERVENTIONS: ORTHOSES
D
Based on conflicting evidence, a recommendation cannot
be made regarding the use of a forearm counterforce or
wrist support orthosis to alleviate intermediate or long-term
symptoms in individuals with LET.
F
Clinicians may use a forearm counterforce or wrist sup-
port orthosis to be worn during activity for immediate im-
provement of pain and strength in those with LET whose
symptoms are aggravated with activity.
INTERVENTIONS: TAPING
B
Clinicians should use rigid taping techniques for immedi-
ate/short-term pain relief and improvement in pain-free
muscle function in those with irritable LET.
C
Clinicians may use kinesiology tape application as part of
a multimodal treatment program for immediate and
short-term management of pain and muscle function in individu-
als with LET.
Journal of Orthopaedic & Sports Physical Therapy®
Downloaded from www.jospt.org at on January 15, 2023. For personal use only. No other uses without permission.
Copyright © 2022 Journal of Orthopaedic & Sports Physical Therapy®. All rights reserved.
journal of orthopaedic & sports physical therapy | volume 52 | number 12 | december 2022 | cpg3
Lateral Elbow Pain and Muscle Function Impairments: Clinical Practice GuidelinesLateral Elbow Pain and Muscle Function Impairments: Clinical Practice Guidelines
INTERVENTIONS: CRYOTHERAPY
C
Clinicians may use cryotherapy combined with burst
transcutaneous electrical nerve stimulation (TENS) to re-
duce pain in the short term in individuals with symptoms of LET
for greater than 30 days.
E
Clinicians may use cryotherapy to reduce pain in individu-
als with irritable symptoms of LET.
INTERVENTIONS: THERAPEUTIC ULTRASOUND
D
Based on conflicting evidence, a recommendation cannot
be made for the use of ultrasound as a stand-alone
treatment.
INTERVENTIONS: PHONOPHORESIS
C
Clinicians should not use phonophoresis with 10% hydro-
cortisone gel, topical prednisolone (2 mg/d), or 1% di-
clofenac sodium gel for the treatment of LET.
INTERVENTIONS: IONTOPHORESIS
C
Clinicians may use iontophoresis with an anti-inflamma-
tory drug, early in the rehabilitation phase (no later than
2-4 weeks from onset or aggravation of symptoms), in individuals
presenting with highly irritable symptoms of LET.
INTERVENTIONS: TENS
C
Clinicians may use burst TENS applied to the painful re-
gion or high- or low-frequency TENS applied to acupunc-
ture points, for short-term pain relief in individuals with LET.
INTERVENTIONS: LASER
C
Clinicians may use laser therapy for improvements in pain
and grip strength, seen in follow-up periods >4 weeks to
6 months, for individuals with LET.
INTEREVENTIONS: ERGONOMICS
E
Clinicians may use ergonomic interventions in the man-
agement of symptoms in individuals with LET; the imple-
mentation of education, behavioral modification, ergonomic
equipment, and workstation adjustments is moderately support-
ed by best practice/standard of care.
*These recommendations and clinical practice guidelines are based on the scien-
tific literature published prior to November 2021.
List of Abbreviations
AHUEPT: Academy of Hand and Upper Extremity
Physical Therapy
APTA: American Physical Therapy Association
ANOVA: analysis of variance
AOPT: Academy of Orthopaedic Physical Therapy
CI: confidence interval
CPG: clinical practice guideline
DASH: Disabilities of the Arm, Shoulder and Hand
DFM: deep friction massage
ECRB: extensor carpi radialis brevis
ES: eect size
GCS: Global Change Scale
GROC: Global Rating of Change
HADS: Hospital Anxiety & Depression Scale
HILT: high-intensity laser therapy
ICC: intraclass correlation coecient
ICD: International Classification of Diseases
ICF: International Classification of Functioning, Disability
and Health
JOSPT: Journal of Orthopaedic & Sports Physical Therapy
LET: lateral elbow tendinopathy
LILT: low-intensity laser therapy
MCID: minimal clinically important dierence
MD: mean dierence
MDC: minimal detectable change
MEPI: Mayo Elbow Performance Index
MRI: magnetic resonance imaging
MRT: manual release therapy
MVIC: maximum voluntary isometric contraction
MWM: mobilization with movement
NPRS: numeric pain-rating scale
OR: odds ratio
PE: percutaneous electrolysis
PFGS: pain-free grip strength
PPT: pressure pain threshold
PRFEQ: Patient-Rated Forearm Evaluation Questionnaire
PROM: patient-reported outcome measure
PRTEE: Patient-Rated Tennis Elbow Evaluation
PRWE: Patient-Rated Wrist Evaluation
PSFS: Patient Specific Functional Scale
RCT: randomized clinical trial
RM: Score: Roles and Maudsley Score
Journal of Orthopaedic & Sports Physical Therapy®
Downloaded from www.jospt.org at on January 15, 2023. For personal use only. No other uses without permission.
Copyright © 2022 Journal of Orthopaedic & Sports Physical Therapy®. All rights reserved.

cpg4 | december 2022 | volume 52 | number 12 | journal of orthopaedic & sports physical therapy
Lateral Elbow Pain and Muscle Function Impairments: Clinical Practice GuidelinesLateral Elbow Pain and Muscle Function Impairments: Clinical Practice Guidelines
ROM: range of motion
RR: relative risk
SD: standard deviation
SEM: standard error of measurement
SMD: standardized mean dierence
SRM: standardized response mean
TDN: trigger point dry needling
TENS: transcutaneous electrical nerve stimulation
UE: upper extremity
US: ultrasound
VAS: visual analog scale
WMD: weighted mean dierence
W/cm
2
: Watts per centimeter squared
Introduction
AIM OF THE GUIDELINES
The Academy of Hand and Upper Extremity Physical Thera-
py (AHUEPT) and Academy of Orthopaedic Physical Ther-
apy (AOPT) of the American Physical Therapy Association
(APTA) have an ongoing eort to create evidence-based
practice guidelines for management of patients with mus-
culoskeletal impairments described in the World Health
Organization’s International Classification of Functioning,
Disability and Health (ICF).
204
The purposes of these clinical guidelines are to:
• Describe evidence-based practice including diagnosis,
prognosis, intervention, and assessment of outcomes of
musculoskeletal disorders commonly managed by ortho-
paedic, sports, and hand physical therapists
• Classify and define common musculoskeletal conditions
using the World Health Organization’s terminology relat-
ed to impairments of body function and body structure,
activity limitations, and participation restrictions
• Identify interventions supported by current best evidence
to address impairments of body function and structure, ac-
tivity limitations, and participation restrictions associated
with common musculoskeletal conditions
• Identify appropriate outcome measures to assess changes
resulting from physical therapy interventions in body func-
tion and structure as well as in activity and participation of
the individual
• Provide a description to policy makers, using internation-
ally accepted terminology, of the practice of orthopaedic,
sports, and hand physical therapists
• Provide information for payers and claims reviewers re-
garding the practice of orthopaedic, sports, and hand ther-
apy for common musculoskeletal conditions
• Create a reference publication for clinicians, academic
instructors, clinical instructors, students, interns, res-
idents, and fellows regarding the best current practice
of orthopaedic and sports physical therapy and hand
rehabilitation
STATEMENT OF INTENT
These guidelines are not intended to be construed or to serve
as a standard of medical care. Standards of care are deter-
mined on the basis of all clinical data available for an individ-
ual patient and are subject to change as scientific knowledge
and technology advance and patterns of care evolve. These
parameters of practice should be considered guidelines only.
Adherence to them will not ensure a successful outcome in
every patient, nor should they be construed as including all
proper methods of care or excluding other acceptable meth-
ods of care aimed at the same results. The ultimate judgment
regarding a particular clinical procedure or treatment plan
must be made in light of the clinical data presented by the
patient, the diagnostic and treatment options available, and
the patient’s values, expectations, and preferences. However,
we suggest that significant departures from accepted guide-
lines should be documented in the patient’s medical records
at the time the relevant clinical decision is made.
SCOPE AND RATIONALE OF THE GUIDELINE
Lateral elbow tendinopathy (LET) is characterized by pain at
the common wrist extensors at or near the lateral epicondyle
that is aggravated by loading of the involved muscles.
13
The
extensor carpi radialis brevis (ECRB) and extensor digitorum
muscles are the most frequently injured,
16
while the pain is be-
lieved to originate from excessive tensile force on the injured
musculotendinous structures and periosteal junction. Lateral
elbow tendinopathy is commonly known as tennis elbow, yet
despite the name, many individuals who present with symp-
toms of LET are not involved in racquet sports.
193
Athletes
of all types and individuals who repetitively use their upper
extremity (UE), particularly involving their wrist extensors,
can be at risk for developing LET. Although many describe
the condition as self-limiting and likely to resolve on its own,
high recurrence rates and extended sick leave highlight the
challenge for the nonsurgical management of individuals
with LET.
14,22
Therefore, there is a need to assemble a com-
prehensive set of guidelines for assessing and treating LET.
Journal of Orthopaedic & Sports Physical Therapy®
Downloaded from www.jospt.org at on January 15, 2023. For personal use only. No other uses without permission.
Copyright © 2022 Journal of Orthopaedic & Sports Physical Therapy®. All rights reserved.

journal of orthopaedic & sports physical therapy | volume 52 | number 12 | december 2022 | cpg5
Lateral Elbow Pain and Muscle Function Impairments: Clinical Practice GuidelinesLateral Elbow Pain and Muscle Function Impairments: Clinical Practice Guidelines
As the understanding of the histology underpinning the ten-
don pathology associated with LET has evolved, clinicians are
beginning to recognize the complexity of the diagnosis. The
interrelationship of histological and structural changes to the
tendon itself, the associated impairments in motor control,
and potential changes in pain processing can all contribute
to the presentation of symptoms in any given individual.
36,59
This clinical practice guideline (CPG) includes studies re-
porting on LET pertinent to physical therapist practice. Ep-
idemiology, functional anatomy and pathophysiology, risk
factors, clinical course, prognosis, dierential diagnosis, tests
and measures, and interventions are included. This CPG ex-
cluded studies that addressed pathologies closely related to
LET. For example, cervical radiculopathy, primary peripheral
nerve entrapment, and joint pathology including plica syn-
drome, radiocapitellar chondromalacia, and posterolateral
rotatory instability as causes of lateral elbow pain were ex-
cluded. Finally, this CPG excluded interventions outside the
scope of physical therapist practice including but not limited
to pharmacological and surgical interventions unless directly
compared to physical therapy management.
Methods
The AHUEPT and the AOPT of the APTA appointed content
experts to develop CPGs for musculoskeletal conditions of
elbow, forearm, wrist, and hand. The aims of this review were
to provide a concise summary of the contemporary evidence
and to develop recommendations to support evidence-based
practice. The authors of this guideline worked with the CPG
editors and medical librarians for methodological guidance.
One author (R.L.M.) served as the team’s methodologist.
Research librarians were chosen for their expertise in sys-
tematic review and rehabilitation literature searching and
to perform systematic searches for concepts associated with
classification, examination, and intervention strategies for
LET. Briefly, the following databases were searched between
January 2001 to November 2021: PubMed including Med-
line, CINAHL, and the Cochrane Library (see
APPENDIX A for
full search strategies, dates, and results, available at www.
jospt.org and www.handpt.org).
The authors declared relationships and developed a con-
flict management plan, which included submitting a con-
flict-of-interest form to the AOPT. Articles authored by
members of the CPG team were assigned to an alternate
reviewer. The AOPT and AHUEPT funded the CPG devel-
opment team for travel and CPG development training. The
CPG development team maintained editorial independence
with regards to the funding agencies.
Articles contributing to recommendations were reviewed
based on prespecified inclusion and exclusion criteria with
the goal of identifying evidence relevant to physical therapist
clinical decision-making for adults with LET. Two members
of the CPG development team independently screened the ti-
tle and abstract prior to full text review to obtain the final set
of articles used to make the recommendations. (See
APPEN-
DIX B for inclusion and exclusion criteria, available at www.
jospt.org and www.handpt.org.) The team leader (A.M.L.)
provided the final decision for discrepancies that were not
resolved by the review team (see
APPENDIX C for the flowchart
of articles, available at www.jospt.org). Data extraction and
assignment of level of evidence was also performed and were
confirmed by members of the CPG development team. For
selected relevant topics for which recommendations were
not developed, which included incidence, risk factors, dier-
ential diagnosis, imaging, and prognosis, articles were not
subject to systematic review process and were not included
in the flowchart. Evidence tables for this CPG are available
on the CPG page of the AOPT of the APTA websites: www.
orthopt.org and www.handpt.org.
This guideline was issued in 2022, based on the published
literature from January 2001 to November 30, 2021, and
will be considered for review in 2027, or sooner if import-
ant evidence becomes available. Any updates to the guide-
line in the interim period will be noted on the AOPT and
AHUEPT of the APTA websites: www.orthopt.org and
www.handpt.org.
LEVELS OF EVIDENCE
Individual clinical research articles were graded according to
criteria adapted from the Centre for Evidence-Based Med-
icine, Oxford, UK (http://www.cebm.net)
25
for diagnostic,
prospective, and therapeutic studies. In teams of 2, each re-
viewer independently assigned a level of evidence and evalu-
ated the quality of each article using a critical appraisal tool.
If the 2 reviewers did not agree on levels of evidence for a
particular article, a third content expert was used to resolve
the issue. (See
APPENDICES D and E for Levels of Evidence table
and details on procedures used for assigning levels of evi-
dence, available at www.jospt.org and www.handpt.org.) The
evidence was organized from the highest to lowest level of
evidence. An abbreviated version of the grading system is
provided in
TABLE 1.
Journal of Orthopaedic & Sports Physical Therapy®
Downloaded from www.jospt.org at on January 15, 2023. For personal use only. No other uses without permission.
Copyright © 2022 Journal of Orthopaedic & Sports Physical Therapy®. All rights reserved.
cpg6 | december 2022 | volume 52 | number 12 | journal of orthopaedic & sports physical therapy
Lateral Elbow Pain and Muscle Function Impairments: Clinical Practice GuidelinesLateral Elbow Pain and Muscle Function Impairments: Clinical Practice Guidelines
GRADES OF EVIDENCE
The overall strength of the evidence supporting recommenda-
tions made in these guidelines was graded according to guide-
lines described by Guyatt et al,
66
as modified by MacDermid
114
and adopted by the coordinator and reviewers of this project.
In this modified system, the typical A, B, C, and D grades of
evidence have been modified to include the role of consensus
expert opinion and basic science research to demonstrate bi-
ological or biomechanical plausibility (
TABLE 2). In developing
their recommendations, the authors considered the strengths
and limitations of the body of evidence and the health bene-
fits, side eects, and risks of tests and interventions.
GUIDELINE REVIEW PROCESS AND VALIDATION
Identified reviewers who are experts in UE injury manage-
ment and rehabilitation reviewed a prepublication draft of
this CPG content and methods for integrity, accuracy, and
that it fully represents the condition. Any comments, sugges-
tions, or feedback from the expert reviewers were delivered
to the author and editors for consideration and appropriate
revisions. These guidelines were also posted for public com-
ment on the AOPT website (www.orthopt.org), and a notifi-
cation of this posting was sent to the members of the AOPT
and AHUEPT. Any comments, suggestions, and feedback
gathered from public commentary were sent to the authors
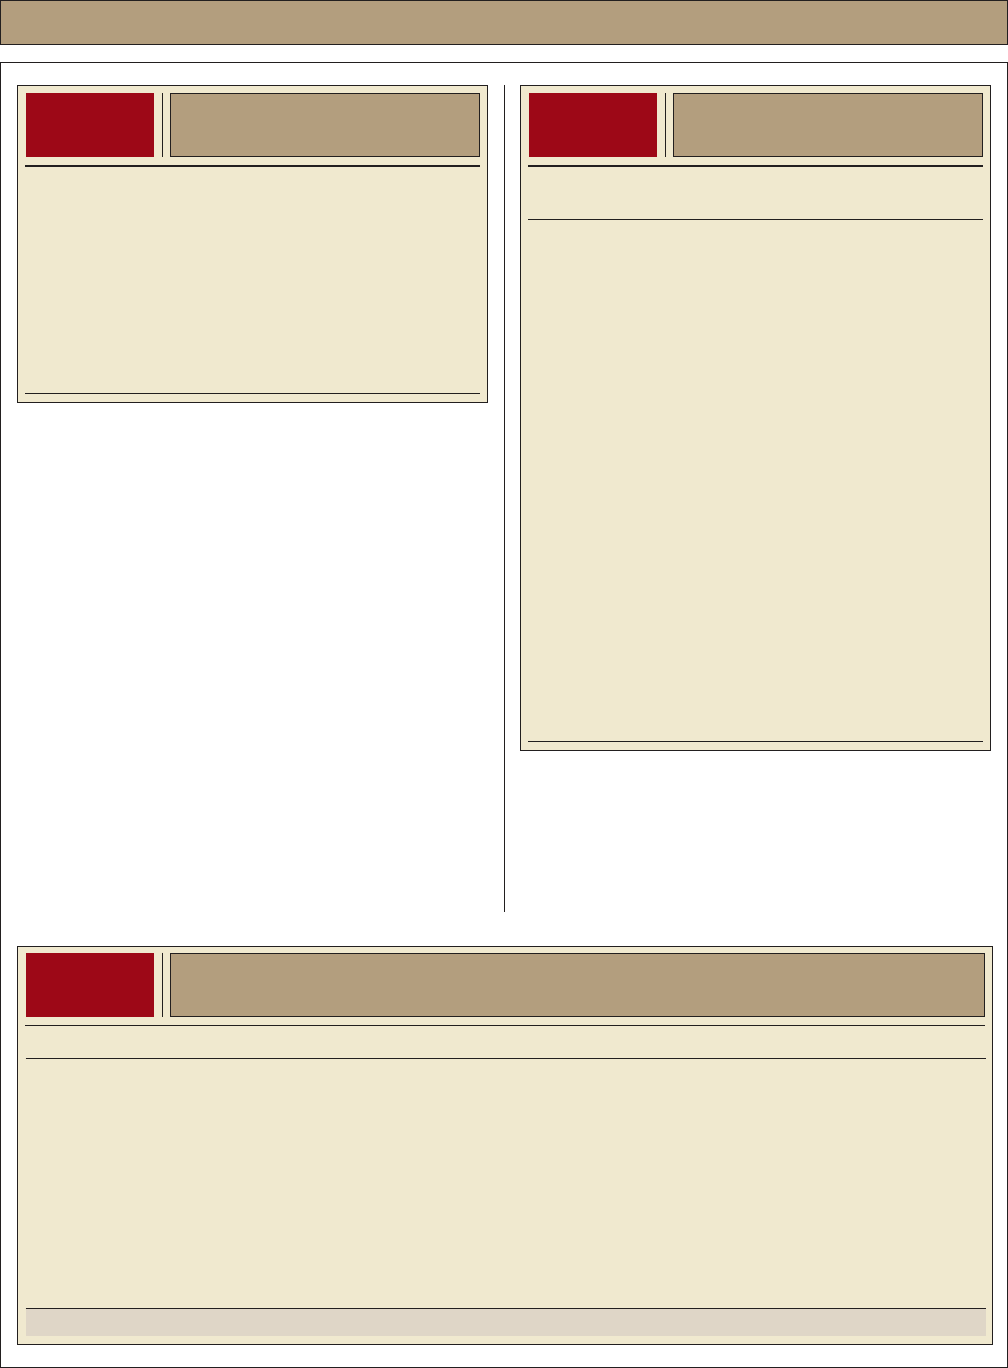
TABLE 1
Levels of Evidence
I Evidence obtained from high-quality diagnostic studies, prospective
studies, systematic reviews, or randomized controlled trials
II Evidence obtained from lesser-quality diagnostic studies, systematic
reviews, prospective studies, or randomized controlled trials (eg, weaker
diagnostic criteria and reference standards, improper randomization, no
blinding, <80% follow-up)
III Case-controlled studies or retrospective studies
IV Case series
V Expert opinion
TABLE 2
Grades of Recommendation
Grades of
Recommendation Strength of Evidence
Level of
Obligation
A Strong evidence A preponderance of level I and/or level
II studies support the recommen-
dation. This must include at least 1
level I study
Must or
should
B Moderate evidence A single high-quality randomized
controlled trial or a preponderance
of level II studies support the recom-
mendation
Should
C Weak evidence A single level II study or a prepon-
derance of level III and IV studies,
including statements of consensus
by content experts, support the
recommendation
May
D Conflicting
evidence
Higher-quality studies conducted on this
topic disagree with respect to their
conclusions. The recommendation is
based on these conflicting studies
E Theoretical/
foundational
evidence
A preponderance of evidence from
animal or cadaver studies, from
conceptual models/principles or
from basic sciences/bench research,
supports this conclusion
May
F Expert opinion Best practice based on the clinical
experience of the guideline develop-
ment team
May
TABLE 3
Planned Strategies and Tools to Support the Dissemination
and Implementation of This CPG
Abbreviations: APTA, American Physical Therapy Association; CPG, clinical practice guideline.
Tool Strategy
JOSPT’s “Perspectives for Patients” and “Perspectives for Practice” articles Patient- and clinician-oriented guideline summaries available at www.jospt.org
Mobile app of guideline-based exercises for patients/clients and health care practitioners Marketing and distribution of app via www.orthopt.org and www.handpt.org
Clinician’s Quick-Reference Guide Summary of guideline recommendations available at www.orthopt.org and www.
handpt.org
JOSPT’s Read for Credit
SM
continuing education units Continuing education units available for physical therapists at www.jospt.org
Webinars and educational oerings for health care practitioners Guideline-based instruction available for practitioners at www.orthopt.org and www.
handpt.org
Mobile and web-based app of guideline for training of health care practitioners Marketing and distribution of app via www.orthopt.org
Non-English versions of the guidelines and guideline implementation tools Development and distribution of translated guidelines and tools to JOSPT’s international
partners and global audience via www.jospt.org
APTA CPG+ Dissemination and implementation aids
Journal of Orthopaedic & Sports Physical Therapy®
Downloaded from www.jospt.org at on January 15, 2023. For personal use only. No other uses without permission.
Copyright © 2022 Journal of Orthopaedic & Sports Physical Therapy®. All rights reserved.

journal of orthopaedic & sports physical therapy | volume 52 | number 12 | december 2022 | cpg7
Lateral Elbow Pain and Muscle Function Impairments: Clinical Practice GuidelinesLateral Elbow Pain and Muscle Function Impairments: Clinical Practice Guidelines
and editors to consider and make appropriate revisions in
the guideline. In addition, a panel of consumer/patient rep-
resentatives and external interested parties, such as claims
reviewers, medical coding experts, academic educators,
clinical educators, physician specialists, and researchers,
also reviewed the guideline and provided feedback and rec-
ommendations that were given to the authors and editors
for further consideration and revisions. The AOPT Clinical
Practice Guideline Advisory Panel reviews guideline devel-
opment methods, policies, and implementation processes on
a yearly basis.
DISSEMINATION AND IMPLEMENTATION TOOLS
In addition to publishing these guidelines in the Journal of
Orthopaedic & Sports Physical Therapy (JOSPT), these guide-
lines will be posted on CPG (free access) areas of the JOSPT,
AOPT, and AHUEPT websites and submitted to be available
for free access on the ECRI Guidelines Trust (guidelines.ecri.
org) and the Physiotherapy Evidence Database (www.PEDro.
org.au). The planned implementation tools for patients, clini-
cians, educators, payers, policy makers, and researchers, and
the associated implementation strategies are listed in
TABLE 3.
ORGANIZATION OF THE GUIDELINE
When systematic reviews were conducted to support specific
actionable recommendations, summaries of studies with the
corresponding evidence levels were followed by evidence syn-
thesis and rationale for the recommendation(s) with harms
and benefits statements and gaps in knowledge. Topics for
which a systematic review was conducted and recommenda-
tions provided include patient-reported outcome measures
(PROMs), physical impairment measures, and interventions.
For other topics where a systematic review was outside the
scope of this CPG, a summary of the literature is provided.
This includes incidence/prevalence, pathoanatomical fea-
tures, risk factors, clinical course, prognosis, diagnostic clas-
sification, and dierential diagnosis, and imaging.
CLASSIFICATION
The primary International Classification of Diseases 10th
Revision (ICD-10) codes and conditions associated with lat-
eral elbow pain and muscle function impairments (LET) are
outlined in
TABLE 4.
TABLE 4
ICD and ICF Codes
Associated With Lateral
Elbow Pain
Abbreviations: ICD, International Classification of Diseases; ICF,
International Classification of Functioning, Disability and Health.
International Statistical Classification of Diseases and Related Health Problems
(ICD-10) 2015
ICD-10 M 7 7. 1 Lateral epicondylitis
International Classification of Functioning, Disability and Health (ICF)
ICF Codes Description
Muscle Function Impairments
b730-b74
b730
b7300
b7301
b740
b7400
b7401
Muscle functions
Muscle power functions
Power of isolated muscles and muscle groups
Power of muscles of one limb
Muscle endurance functions
Endurance of isolated muscles
Endurance of muscle groups
Pain
b280
b28014
Sensation of pain
Pain in upper limb
Motor Control Impairments
b1471
b760
b7602
b7603
Quality of psychomotor functions
Control of voluntary movement functions
Coordination of voluntary movements
Supportive functions of arm or leg
Activity Limitations
d445
d4453
d430
d4300
d440
d4400
d4454
Hand and arm use
Turning or twisting the hands or arms
Lifting and carrying objects
Lifting
Fine hand use
Picking up
Throwing
Participation Restrictions
d920
d9201
d840-d859
d850
d8500
d8501
d8502
d855
Recreation and leisure
Sports
Work and employment
Remunerative employment
Self-employment
Part-time employment
Full-time employment
Nonremunerative employment
Journal of Orthopaedic & Sports Physical Therapy®
Downloaded from www.jospt.org at on January 15, 2023. For personal use only. No other uses without permission.
Copyright © 2022 Journal of Orthopaedic & Sports Physical Therapy®. All rights reserved.

cpg8 | december 2022 | volume 52 | number 12 | journal of orthopaedic & sports physical therapy
Lateral Elbow Pain and Muscle Function Impairments: Clinical Practice GuidelinesLateral Elbow Pain and Muscle Function Impairments: Clinical Practice Guidelines
CLINICAL PRACTICE GUIDELINES
Impairment/Function-Based Diagnosis
PREVALENCE/INCIDENCE
A large population-based study suggested an overall annual
incidence of LET in the United States of 3%, although the
rates for those 40-60 years old were higher, ranging between
7% and 10%.
158
The prevalence of LET has been reported to
be as high as 29% in workers in occupations that required
a high demand of wrist and hand movements.
170,198
A 2015
systematic review of UE work-related musculoskeletal dis-
orders reports LET incidence ranges from 0.45 to 7 new
cases per 100 workers and prevalence ranges from 1 to 12.2
new cases per 100 workers.
40
An average of 12 weeks of sick
leave from work is taken in approximately 30% of those in-
dividuals with LET.
13,17
Additionally, incomplete resolution
or recurrence of symptoms at 6-12 months in individuals
receiving local nonsurgical management has been shown to
range between 20% and 38%.
16
At 2 years follow-up, the rate
of recurrence has been shown to be as high as 54%.
134
In
tennis players, the 2-month prevalence has been reported
at 14%, with recurrent cases being more common than new
cases, and rates increasing in players over 40 years of age.
65
A twin study estimated that heritability was 40%, after ad-
justing for age.
197
Pathoanatomical Features
The lateral epicondyle of the humerus, located just above
the capitellum, is the origin of the extensor-supinator mus-
cles.
126,130
The most common site of pathology in LET is the
juncture of the common extensor muscle origin of the lateral
epicondyle.
99
The enthesis or insertion of the common ex-
tensor tendon is characterized by a load sharing mechanism
where fibers of the ECRB tendon fuses with the lateral collat-
eral ligament of the elbow and joint capsule and subsequent-
ly with the annular ligament of the proximal radial ulnar
joint.
125
Stress is dissipated throughout the entire enthesis
organ and may explain the somewhat diuse distribution of
pain at the lateral elbow with LET.
12
The common extensor tendon of the wrist and fingers at the
elbow may be injured not only by repetitive tensile loading
but also by shearing forces against the capitellum with fore-
arm rotation.
23
The ECRB tendon has a unique anatomic lo-
cation that makes its undersurface vulnerable to contact and
abrasion against the lateral edge of the capitellum during
forearm pronation and supination.
275
Relative hypovascular-
ity of the ECRB tendon may further contribute to the sus-
ceptibility of the tendon to injury and may negatively impact
healing.
8,161
The extensor carpi radialis longus and extensor
digitorum tendons may also be involved. This may explain
why repetitive loading of the elbow, forearm, wrist, and/or
digits during work or athletic activities increases the risk of
LET.
48,171
However, similar biomechanical loading can poten-
tially injure adjacent structures; therefore, a thorough exam-
ination is required to dierentiate lateral elbow pain caused
by tendinopathy from other sources of symptoms such as
muscle, joint, or nerve pathology.
There has been a shift in understanding of tendon pathology
over the past 20 years. Tendinopathy refers to a nonrupture
injury in the tendon or peritendon (paratenon and epitenon)
that is aggravated by mechanical loading.
62
The term tendini-
tis characterizes an acute condition with a cell-mediated in-
flammatory response. Tendinosis is a term that has been used
to describe chronic degenerative tendon pathology, charac-
terized by an abundance of fibroblasts, vascular hyperplasia,
and unstructured collagen. Over time, clinical terminology
has changed from tendinitis or tendinosis to tendinopathy,
which represents the pain and impaired muscle function re-
lated to a broad spectrum of potential intratendinous changes
in structure, histology, and chemical mediators of pain and/
or inflammation.
58
In those with LET, as with other forms of
tendinopathy, individuals present somewhere in the continu-
um between acute and chronic conditions that may fluctuate
over an episode of care. Therefore, it is possible that low-grade
inflammation may be intermittent and may occur for short
periods after intense tendon loading in chronic situations
characterizing an acute-on-chronic condition in some cases.
It has been postulated that LET is acquired by irritation of
the hypovascular zone of the common extensor tendon at its
attachment on the lateral epicondyle, which leads to subse-
quent neovascularization
45
that has been described as “an-
giofibroblastic tendinosis.”
99
Chronic LET is characterized by
Journal of Orthopaedic & Sports Physical Therapy®
Downloaded from www.jospt.org at on January 15, 2023. For personal use only. No other uses without permission.
Copyright © 2022 Journal of Orthopaedic & Sports Physical Therapy®. All rights reserved.

journal of orthopaedic & sports physical therapy | volume 52 | number 12 | december 2022 | cpg9
Lateral Elbow Pain and Muscle Function Impairments: Clinical Practice GuidelinesLateral Elbow Pain and Muscle Function Impairments: Clinical Practice Guidelines
disorganization of collagen fibers, an increase in the number
of vessels and sensory nerves, disorganized (smaller) type III
collagen fibers,
161
and areas of hypocellularity or fibroblast
reaction.
13,162
It is important to recognize that, despite the
lack of consistent evidence relating to the presence or ab-
sence of inflammatory cells locally,
88
other proinflammatory
chemical agents including inflammatory cytokines, growth
factors, prostaglandins, and neuropeptides have been detect-
ed in cases of chronic tendinopathy.
62
Neurochemicals are
important in the regulation of local tendon vascular supply
but are also believed to contribute to neurogenic inflamma-
tion. More recent evidence also points to altered nociceptive
processing as a contributor to persistent pain associated with
LET.
15,37
Preliminary evidence highlights the association of
nervous system sensitization in patients with chronic ten-
dinopathy.
147
It is important to appreciate the hypothesized
underlying tissue pathology in the context of the complex
processes related to the neuromodulation of pain, both pe-
ripherally and centrally.
59
The complex underlying pathophysiologic mechanisms asso-
ciated with LET may explain why it is dicult to accurately
classify and subgroup individuals with LET in a single/simple
classification system and may also explain why its symptoms
are sometimes dicult to bring to full resolution. It is import-
ant to assess the intensity, irritability, and distribution of the
individual’s symptoms while considering their history and their
required activity levels to properly manage the condition.
113
SUMMARY
Most pathological changes in LET occur within the common
extensor tendon origin at the lateral epicondyle, common-
ly within the fibers associated with the ECRB muscle. It is
known that structural, cellular, and chemical alterations in
the tendon can all exist with tendinopathy, but do not nec-
essarily correspond with the severity of clinical presentation.
Clinicians should recognize that histological confirmation of
the underlying pathophysiology in LET for any patient is not
realistic in practice settings. Therefore, the acuity, irritability,
and the severity of LET symptoms at any given time should
guide management of this condition. In chronic cases of LET,
intense loading of the tendon with activity may result in low
grades of inflammation creating an acute aggravation of a
chronic condition.
Risk Factors
For this CPG, the term risk will be reserved specifically for
risk factors for new onset of LET, whereas prognosis (dis-
cussed later) will refer to the predicted course of the condi-
tion after onset. A systematic review of 5 prospective cohort
studies found a significant association between combined
biomechanical exposure involving the wrist and elbow and
incidence of LET (pooled odds ratio [OR] = 2.6; 95% CI:
1.9, 3.5).
47
A case-control study that included the general
population with a diagnosis of LET reported a higher risk
for women for handling tools >1 kg (women OR = 3.0; 95%
CI: 1.6, 5.5; men OR = 2.1; 95% CI: 1.1, 3.8).
68
Shiri et al,
171
in
their cross-sectional cohort study, found a significant associ-
ation between LET and jobs that involve handling loads >20
kg at least 10 times/day for more than 20 years in a cohort
of working population from a national registry (OR = 2.6;
95% CI: 1.3, 5.1).
After adjusting for age, lack of social support, and obesity in
a cohort of more than 1000 newly employed workers without
symptoms of LET, those who reported wrist bending/twist-
ing and forearm twisting/rotating/screwing motion were at
elevated risk of developing LET.
48
Hard perceived physical
exertion combined with elbow flexion/extension (>2 hours/
day) (men OR = 2.6; 95% CI: 1.9, 3.7) and wrist bending (>2
hours/day) (men OR = 5.6; 95% CI: 2.8, 11.3 and women OR
= 2.9; 95% CI: 1.3, 6.5) was found to be significant risk factors
for LET.
78
In a population-based study, significant associa-
tions between LET and repetitive movements of the hand or
wrist for at least 2 hours/day for those with 9 to 19 years ex-
posure (OR = 2.4; 95% CI: 1.2, 4.9) and for 20 or more years
of exposure (OR = 2.8; 95% CI: 1.4, 5.8) were identified.
171
Park et al,
141
in their case-control study that included 937 par-
ticipants from a rural agricultural setting, found significant
associations between LET and dominant-side involvement
(OR = 3.21; 95% CI: 2.24, 4.60), female sex (OR = 2.47; 95%
CI: 1.78, 3.43), manual labor (OR = 2.25; 95% CI: 1.48, 3.43),
and ipsilateral rotator cu tear (OR = 2.77; 95% CI: 1.96,
3.91).
141
Another study that included 1824 workers found a
significant association between cardiovascular disease and
LET symptoms (OR = 3.81; 95% CI: 2.11, 6.85), positive ex-
amination findings for LET (OR = 2.85; 95% CI: 1.59, 5.12),
and combined symptoms and physical examination (OR =
6.20; 95% CI: 2.04, 18.82).
76
In a case-control study
183
of 4998 patients with LET matched
by age/sex from general practice settings, a multivariate
analysis identified significant association between LET and
Journal of Orthopaedic & Sports Physical Therapy®
Downloaded from www.jospt.org at on January 15, 2023. For personal use only. No other uses without permission.
Copyright © 2022 Journal of Orthopaedic & Sports Physical Therapy®. All rights reserved.

cpg10 | december 2022 | volume 52 | number 12 | journal of orthopaedic & sports physical therapy
Lateral Elbow Pain and Muscle Function Impairments: Clinical Practice GuidelinesLateral Elbow Pain and Muscle Function Impairments: Clinical Practice Guidelines
rotator cu pathology (OR = 4.95; 95% CI: 3.64, 6.71), De
Quervain’s disease (OR = 2.48; 95% CI: 1.14, 5.37), carpal
tunnel syndrome (OR = 1.50; 95% CI: 1.14, 1.98), oral corti-
costeroid therapy (OR = 1.68; 95% CI: 1.47, 1.92), and pre-
vious smoking history (OR = 1.20; 95% CI: 1.06, 1.36). In
addition, diabetes mellitus, current smoking, trigger finger,
rheumatoid arthritis, alcohol intake, and obesity were deter-
mined not to be associated with LET.
183
An earlier systematic
review
190
of 13 studies identified associations between LET
and the psychosocial risk factors of low control over work
duties (OR = 2.2; 95% CI: 1.4, 3.2) and low social support
(OR = 1.8; 95% CI: 1.2, 2.7).
190
SUMMARY
Female sex, dominant-side involvement, previous smoking
history, rotator cu injuries, De Quervain’s disease, carpal
tunnel syndrome, and oral corticosteroid therapy use rep-
resent nonmodifiable risk factors for LET. Modifiable risk
factors for LET include low job control, low social support,
handling heavy tools greater than 20 kg, repetitive elbow/
wrist flexion/extension for more than 2 hours a day, and
repetitive forearm twisting/rotating/screwing movements.
Diabetes, trigger finger, rheumatoid arthritis, alcohol in-
take, and obesity were not associated with the incidence
of LET.
Clinical Course
Lateral elbow tendinopathy can be a source of lasting pain
and disability for many individuals. The clinical course of
LET depends heavily on the extent to which individuals are
exposed to repetitive irritation of the involved structures.
While some experience full and expedient resolution of
symptoms with nonsurgical care, more than half of patients
seeking general medical care continue to report symptoms
after 1 year.
14
Regardless of past treatments, up to 20% of in-
dividuals report persistent pain for 3-5 years after care.
35
Ex-
posure to various occupational or sports-specific stresses, as
in tennis, may negatively impact prognosis and can result in
lost work time due to injury.
198
Up to 55% of individuals with
LET have been shown to have lingering pain and functional
loss for more than 2 years after the onset of symptoms.
133
Therefore, LET may not always follow the typical course and
time frames of the normal healing process. By the time an
individual seeks medical care, the inflammatory process has
often resolved, yet symptoms remain.
The age- and sex-adjusted annual incidence of LET in the
general population has decreased significantly over time
from 4.5/1000 people in 2000 to 2.4/1000 in 2012.
158
On
the other hand, the proportion of surgically treated cases has
tripled (1.1% in 2000-2002 to 3.2% from 2009 to 2011).
158
About 1 in 10 patients with persistent symptoms at 6 months
were treated with surgery.
158
The course of the tendinopathy is important to consider as a
descriptive element as this can range from a single isolated
initial episode to a re-occurrence, to an episodic condition, or
it may be persistent. In persistent chronic LET, exacerbations
are typically associated with an activity that in some cases
may be predicted based on the amount and nature of the
activity. Determining level of irritability by using pain level,
distribution of pain, and level of disability can be useful in
directing treatment.
SUMMARY
Although many believe the condition to be benign, LET can
be debilitating for some individuals, resulting in an inability
to fully perform their job, household tasks, or athletic in-
terests. Nonsurgical interventions are the mainstay of LET
management. While some individuals can fully and quickly
recover, many experience persistent pain or recurrence of
symptoms, contributing to a poor prognosis regarding pro-
longed discomfort. Protection from repetitive irritation may
help minimize or eliminate exacerbations or recurrence of
symptoms.
Journal of Orthopaedic & Sports Physical Therapy®
Downloaded from www.jospt.org at on January 15, 2023. For personal use only. No other uses without permission.
Copyright © 2022 Journal of Orthopaedic & Sports Physical Therapy®. All rights reserved.

journal of orthopaedic & sports physical therapy | volume 52 | number 12 | december 2022 | cpg11
Lateral Elbow Pain and Muscle Function Impairments: Clinical Practice GuidelinesLateral Elbow Pain and Muscle Function Impairments: Clinical Practice Guidelines
Prognosis
Prognosis refers to the predicted course of LET after its
onset. Some factors may assist the clinician in predicting
short-term physical therapy treatment outcome, as well as
the eventual long-term outcome of LET management.
Analysis of data from a randomized control trial (RCT) with
62 subjects (mean age = 48.2 years) undergoing physical
therapy that consisted of 5 treatment sessions of mobilization
with movement (MWM) and exercise, found several factors
at baseline associated with improved outcomes.
195
Age <49
years, pain-free grip strength (PFGS) >112 N on the aected
side, and PFGS <336 N on the unaected side predicted a
self-report of symptoms being improved at 3 weeks (P<.01,
Nagelkerke’s R
2
= 0.45). The probability of improvement was
87%, 93%, and 100% if one, two, or three of the indicators
were present, respectively.
195
The authors of a multicenter prospective trial with 83 sub-
jects (mean age = 44.2 years; 47 women, 36 men) under-
going physical therapy, consisting of 10 visits over 8 weeks
with ultrasound (US), soft tissue massage, stretching,
and strengthening components, determined predictors of
8-week outcomes.
201
Predictors for greater disability (r
2
=
0.61, P = .0001) included higher baseline Disabilities of the
Arm, Shoulder and Hand (DASH) scores (β = .50; 95% CI:
0.34, 0.66), sex (female) (β = 8.92; 95% CI: 3.3, 14.5), and
self-reported nerve symptoms (β = 7.32; 95% CI: 0.8, 13.8).
Predictors for higher pain visual analog scale (VAS) scores
(r
2
= 0.31, P = .0003) included baseline pain VAS (β = .19;
95% CI: 0.01, 0.37), sex (female) (β = 9.26; 95% CI: 0.4,
18.2), and self-reported nerve symptoms (β = 15.08; 95%
CI: 4.7, 25.5). Age, duration of symptoms, elbow joint signs,
cervical joint signs, and jobs with repetition did not contrib-
ute to the prognostic models (P>.05).
201
Follow-up on these
subjects at 6 months found performing a repetitive job to
be the best predictor for higher DASH (r
2
= 0.52, P = .0001)
and pain VAS (r
2
= 0.14, P = .0151) scores.
200
Similar findings
related to type of occupation were noted by Paoloni et al
140
and Lewis et al,
107
as those performing manual labor jobs
were less likely to improve by 6 months.
Prognostic factors were examined in 131 subjects (mean
age = 44 years; 80 females, 51 males) who were followed
after initiation of conservative treatment that consisted of
self-stretching and use of a counterforce brace.
153
Increased
patient-reported disability on the DASH at 6 months was
associated with initial lower pain thresholds to pressure (β =
−1.28; 95% CI: −1.79, −0.78), initial higher (increased) pain
sensitivity (Pain Sensitivity Questionnaire) scores (β = 1.69;
95% CI: 0.92, 2.49), and involvement in a manual labor job
(β = 1.12; 95% CI: 0.84, 1.41). These 3 factors accounted for
36% of the variance in 6-month DASH scores.
153
Analysis from an RCT of 266 subjects (163 were >40 years of
age; 144 females, 122 males) found that the primary factor
associated with pain reduction less than 50% at 1-year fol-
low-up was LET on the dominant side (OR = 3.1; 95% CI:
1.4, 6.8). Age, being greater or less than 40 years of age, and
sex were not significant prognostic factors.
67
Similarly, Hol-
medal et al
81
also found when looking at 177 subjects (mean
age = 47 years; 71 women, 106 men) in an RCT, age, sex,
and duration of symptoms not to be significant (P>.05) in
predicting treatment success, as defined by a report of be-
ing much better or completely recovered, at 26- or 52-week
follow-up.
A prospective international study followed 349 subjects
(mean age = 48 years, 171 females, 178 males) from 2 RCTs
investigating conservative interventions for LET in a primary
care setting. These authors noted a combination of 20 prog-
nostic variables, including the covariates country and treat-
ment, contributed to only 12% of the variance in predicting
pain intensity at 12-month follow-up.
205
SUMMARY
When looking at the eect of physical therapy interventions
in short term follow-up, grip strength and age were found
to be useful in predicting 3-week outcomes, whereas base-
line disability, female sex, and self-reported nerve symptoms
may be useful in predicting 8-week outcomes. For 6-month
follow-up, occupation may be important to consider as re-
petitive and manual labor jobs may help in predicting those
with a potential for poorer outcomes. When looking at all
individuals independent of treatment, the involvement of the
dominant arm may be useful in predicting outcomes at 1 year.
However, predicting long-term outcomes may generally be
challenging, as prognostic variables do not seem to accurately
predict outcomes.
Journal of Orthopaedic & Sports Physical Therapy®
Downloaded from www.jospt.org at on January 15, 2023. For personal use only. No other uses without permission.
Copyright © 2022 Journal of Orthopaedic & Sports Physical Therapy®. All rights reserved.
cpg12 | december 2022 | volume 52 | number 12 | journal of orthopaedic & sports physical therapy
Lateral Elbow Pain and Muscle Function Impairments: Clinical Practice GuidelinesLateral Elbow Pain and Muscle Function Impairments: Clinical Practice Guidelines
Diagnosis/Classification
OVERVIEW
An accurate diagnosis of LET is very important to provide ade-
quate and appropriate treatment. Diagnosis and classification of
LET is based on adequate history taking, physical findings, and
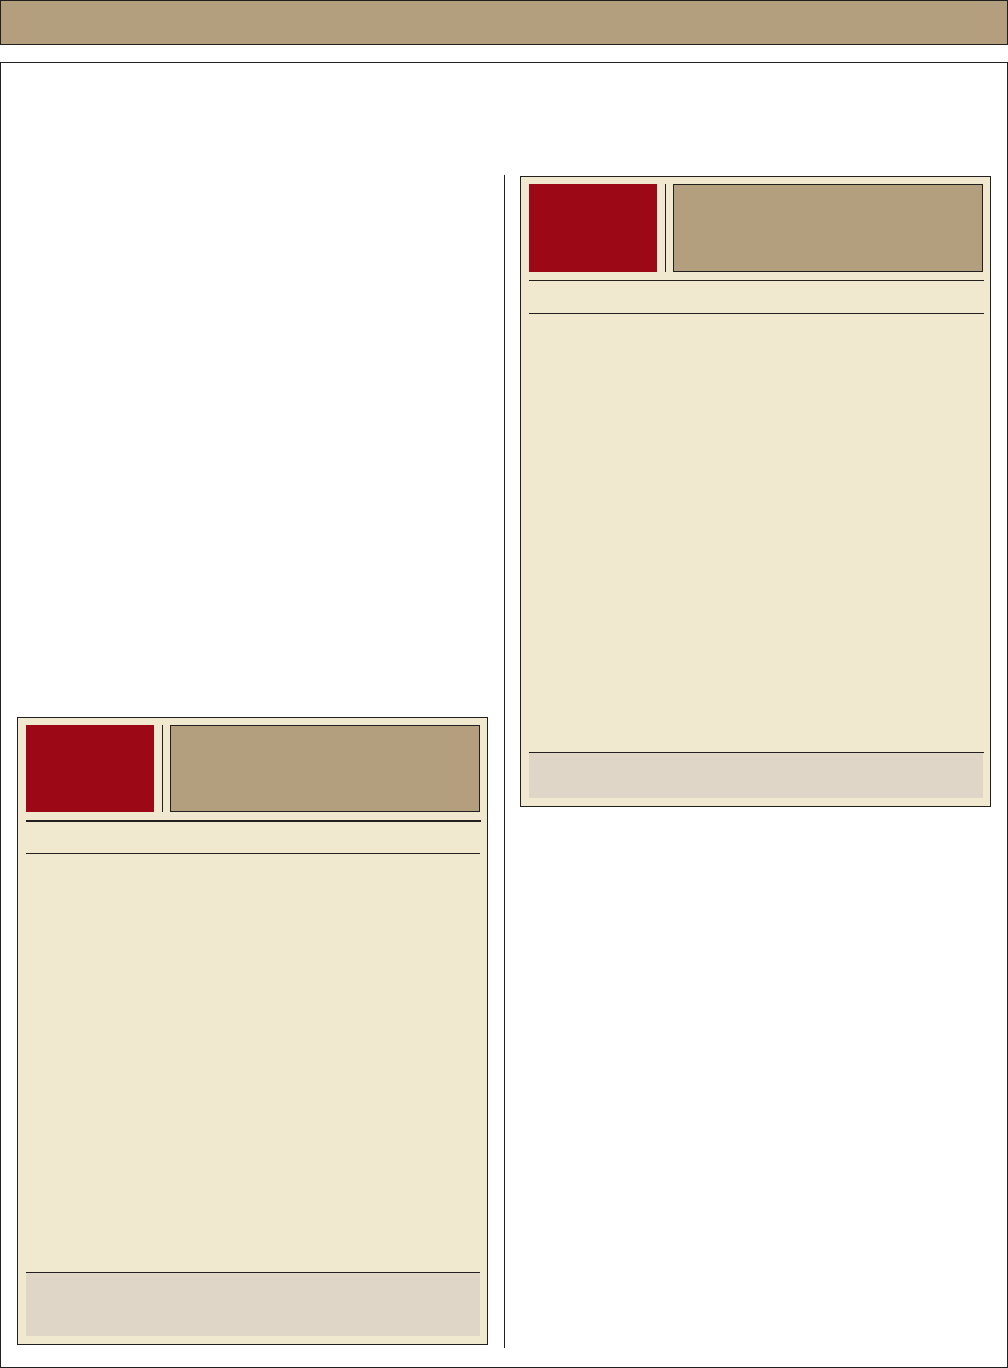
special tests (
TABLES 5-7). An accurate diagnosis with a better un-
derstanding of the classification of LET may aid in planning a re-
turn to work and activity and may help prevent future reinjuries.
CLASSIFICATION
Classification systems are typically designed as descriptive
tools, although ideally, they would be useful in directing ap-
propriate treatment or predicting outcomes. However, limited
research exists to support the use of reported classification
systems related to tendinopathy in general and LET in specif-
ic. Most classification systems proposed are based on the acu-
ity, severity, and irritability of LET individually as stand-alone
classifications or a combination of these dimensions.
20,135,162,203
Making the classification of LET even more challenging, in-
dividuals with dierent occupational or athletic demands and
those with multiple recurrences tend to vary in their response
to interventions. MacDermid and Silbernagel
113
proposed a
descriptive classification (
TABLE 8) that considers 6 classifi-
cation axes, including irritability and distribution of symp-
toms while including descriptive information on the context
(general population, sports, worker’s compensation, etc), the
acuity, the likely underlying pathology (usually determined
by imaging), and the course (recurrent vs isolated episode or
persistent symptoms). This, when used appropriately, would
provide the clinician with a holistic picture of patients with
LET and can be eective in tracking progress and guiding
treatment. For example, when determining the stage of irri-
tability, self-reported pain scores (NRPS) help quantify pain
intensity as either mild intensity (≤3/10), moderate intensity
(4-6/10), or severe intensity ≥7/10). Distribution of symptoms
can be classified as unilateral and localized to the lateral epi-
condyle (type 1), bilateral and localized to the lateral epicon-
dyles (type 2), or diuse symptoms at the elbow along with
cervical or diuse UE pain or neuropathic pain (type 3).
An assessment of how symptom irritability aects function
using PTREE scores can indicate mild disability (score of
Abbreviations: ECRB, extensor carpi radialis brevis; ICF, International
Classification of Functioning, Disability and Health; LET, lateral elbow
tendinopathy.
TABLE 5
Resisted Middle
Finger Extension Test
(Maudsley’s Test)
117
ICF Category Measurement of Impairment of Body Function
Description Special test to assist with the diagnosis of LET
Measurement method Patient position:
The patient can be in sitting or standing with the elbow
in full extension, forearm pronation, and fingers in
extension.
Test:
The examiner supports the distal end of the forearm and
applies resistance to the dorsum of the distal phalanx
of the third digit of the hand, indirectly stressing the
ECRB muscle and tendon.
Positive test:
Reproduction of pain at the lateral epicondyle of the hu-
merus or within 2 cm distal to the common extensor
tendon insertion site.
Nature of variable Nominal/dichotomous
Units of measurement None
Measurement properties Maudsley’s test showed little association with pressure
pain threshold (β = .293).
145
Sensitivity = 88%
159
Sensitivity = 66%; 95% CI: 53%, 76%
51
Abbreviations: ICF, International Classification of Functioning, Dis-
ability and Health; LET, lateral elbow tendinopathy.
TABLE 6
Resisted Wrist Extension
Test or Cozen’s Test
or LET Test
117
ICF Category Measurement of Impairment of Body Function
Description Special test to assist with the diagnosis of LET
Measurement method Patient position:
The patient can be in sitting or standing with the elbow
fully extended, forearm pronated, and the wrist
extended to 30°.
Test:
The patient’s elbow is stabilized by the examiner’s
thumb, which rests on the patient’s lateral epicon-
dyle. The examiner then provides pressure to the
dorsum of the second and third metacarpals using
the other hand to resist active wrist extension.
Positive test:
Reproduction of pain at the lateral epicondyle of the hu-
merus or within 2 cm distal to the common extensor
tendon insertion site.
Nature of variable Nominal/dichotomous
Units of measurement None
Measurement properties Cozen’s test showed fair association with pressure pain
threshold (β = .436).
145
Sensitivity = 84%
159
Sensitivity = 91%; 95% CI: 81%, 96%
51
Journal of Orthopaedic & Sports Physical Therapy®
Downloaded from www.jospt.org at on January 15, 2023. For personal use only. No other uses without permission.
Copyright © 2022 Journal of Orthopaedic & Sports Physical Therapy®. All rights reserved.

journal of orthopaedic & sports physical therapy | volume 52 | number 12 | december 2022 | cpg13
Lateral Elbow Pain and Muscle Function Impairments: Clinical Practice GuidelinesLateral Elbow Pain and Muscle Function Impairments: Clinical Practice Guidelines
<20/50), moderate disability (score between 21 and 34/50),
or severe disability (score >30). The presentation of symp-
toms can fluctuate widely depending on the individual’s oc-
cupational or athletic demands during treatment.
As systems for subclassifying LET evolve and become validat-
ed, it may be possible to direct treatment to more eectively
manage symptoms in specific subpopulations of individuals
with LET. Physical therapists may document the classifica-
tion of LET considering context, acuity, pathology, course,
distribution of symptoms, and irritability, and consider these
factors in treatment planning. Empirical validation of clas-
sification systems is needed to better guide treatment and
future research initiatives.
SUMMARY
An accurate clinical diagnosis of LET is very important to
plan treatment and to prevent recurrence. The ICD diagnosis
of LET and the associated ICF diagnosis of pain and muscle
function impairments are typically made when, on clinical
examination, the patient presents with reports of pain local
to the lateral epicondyle reproduced with palpation, resist-
ed wrist and/or digit extension, and stretch/elongation of
the long wrist extensors. There are 3 common special tests
(Maudsley’s, Cozen’s, and Mill’s stretch) that are used to
arrive at a clinical diagnosis of LET. These tests have weak
evidence supporting their diagnostic usefulness.
188,211
More
problematic in the clinical diagnosis of LET is that sever-
al other pathologies result in a similar distribution of pain;
therefore, a thorough physical examination based on the ex-
clusion of other disorders as the cause of lateral elbow pain is
especially important for a more confident diagnosis of LET.
The classification system that is presented here can be uti-
lized. However, research is required to validate classification
systems and to assess their eectiveness on outcomes. Scien-
tific inquiry into the value of subclassifying individuals into
groups to allow for intervention-matching is needed.
The CPG team feels that the classification of patients with
LET based on level of irritability can be useful to direct treat-
ment. Self-reported pain, distribution of symptoms, and level
of disability should all be considered in the stage of irrita-
bility. For those who have severe pain, type 3 distribution,
and high disability, the focus of treatment can be on symp-
tom modulation. Joint and soft-tissue mobility is the focus
of treatment for those with moderate pain, type 3 distribu-
tion, and moderate disability. When mild pain with type 1-2
distribution and low disability is achieved, loading the wrist
extensors can be done while return to function can be the
focus of treatment for those with mild-absent pain, type 1-2
distribution, and mild-absent disability. It should be noted
that shifting between categories is fluid and patients may of-
ten fit more than one category at a given time.
DIFFERENTIAL DIAGNOSIS
Physical therapists should be able to identify other musculo-
skeletal and nonmusculoskeletal conditions that mimic the
clinical presentation of LET and promptly refer patients to
other health care professionals for further evaluation and
management, if appropriate. The steps in developing a dier-
ential diagnosis include history taking, physical examination
(including proper examination of special tests), and possibly,
imaging. The conditions to consider with a dierential diag-
nosis of lateral elbow pain, although not all-inclusive, include
the following:
• Cervical radiculopathy
103
• Radial tunnel syndrome
54,154
• Posterior interosseous syndrome
69
• Plica syndrome
156,176
• Radio-capitellar chondromalacia,
104
• Posterolateral rotatory instability
90
• Myofascial trigger points in the wrist extensors
71
History and physical exam findings are considered the gold
standard used to confirm the diagnosis. Imaging, however,
can be useful in evaluating the extent of disease, identifying
associated pathology, and excluding other sources of elbow
pain; particularly in cases where initial nonsurgical treat-
ment is unsuccessful. For refractory cases of LET, initial im-
aging should include radiographs. Radiographs are usually
negative but may demonstrate calcium deposition adjacent
to the lateral epicondyle and can be used to exclude other
Abbreviations: ICF, International Classification of Functioning, Dis-
ability and Health; LET, lateral elbow tendinopathy.
TABLE 7
Mill’s Stretch Test or
Long Extensor Stretch
124
ICF Category Measurement of impairment of body function
Description Special test to assist with the diagnosis of LET
Measurement method Patient position:
The patient can be in sitting or standing beginning with the
elbow flexed to 90°, with the forearm pronated, and the
wrist fully flexed.
Test:
The examiner extends the elbow slowly while palpating the
lateral epicondyle.
Positive test:
Reproduction of pain at the lateral epicondyle of the
humerus or within 2 cm distal to the common extensor
tendon insertion site.
Nature of variable Nominal/dichotomous
Units of measurement None
Measurement
properties
Mill’s test showed little association with pressure pain
threshold (β = .267).
145
Sensitivity = 53%; Specificity = 100%
159
Sensitivity = 76%; 95% CI: 63%, 85%
51
Journal of Orthopaedic & Sports Physical Therapy®
Downloaded from www.jospt.org at on January 15, 2023. For personal use only. No other uses without permission.
Copyright © 2022 Journal of Orthopaedic & Sports Physical Therapy®. All rights reserved.

cpg14 | december 2022 | volume 52 | number 12 | journal of orthopaedic & sports physical therapy
Lateral Elbow Pain and Muscle Function Impairments: Clinical Practice GuidelinesLateral Elbow Pain and Muscle Function Impairments: Clinical Practice Guidelines
pathologies. The advanced imaging modality most widely
used is magnetic resonance imaging (MRI), followed by US.
71
The sensitivity of MRI in detecting LET is reported to range
between 90% and 100% and specificity from 83% to 100%.
123
Classic MRI findings include increased signal within or
around the common extensor tendon, a discrete collection of
fluid between the common extensor tendon and radial col-
lateral ligament, and tendon thickening.
149
A meta-analysis
demonstrated that MRI signal change occurred in 90% of el-
bows with a clinical diagnosis of LET compared to only 14% of
controls.
142
Magnetic resonance imaging is often used to grade
the severity of disease (mild, moderate, and severe).
26
While
some authors report no statistically significant association
between imaging measures and symptoms,
31,199
Qi et al
149
re-
ported a positive correlation between the grade of tendinopa-
thy and patient-reported pain and disability. When combined
with an appropriate clinical assessment, MRI can be useful in
establishing a plan of care for individuals with LET.
87
Ultrasound can also be used to evaluate LET.
71
Findings in-
clude tendon thickening and tendon heterogeneity, tendon
tears (hypoechoic regions), and tendon discontinuity.
31
Sur-
rounding fluid and calcification can also be detected. A sys-
tematic review
52
examining the diagnostic accuracy of US in
LET found that hypoechogenicity of the common extensor
origin was both moderately sensitive (0.64; 95% CI: 0.56,
0.72) and highly specific (0.82; 95% CI: 0.72, 0.90) in deter-
mining which elbows had LET. Ultrasound features of chron-
ic LET that showed high specificity included neovascularity
(specificity, 1.00; 95% CI: 0.97, 1.00), calcifications (0.97;
95% CI: 0.94, 0.99), and cortical irregularities (0.96; 95%
TABLE 8
Descriptive Classification of Lateral Elbow Tendinopathy
a
VAS Pain Score ______ PRTEE Pain Score ______ PRTEE Total score ______
^The highest stage the person is most aligned with preferably defined by validated pain and disability measures
*Mild pain: ≤3/10 on VAS; 20/50 on PRTEE pain scale and 40/100 on PRTEE full scale
**Moderate Pain: 4-6/10 VAS; 21-34/50 on PRTEE pain scale and 41-69/100 on PRTEE full scale
***Severe Pain: >7/10 VAS; >36/50 on PRTEE pain scale and >70/100 on PRTEE full scale
a
Table adapted with permission from Joy MacDermid.
Axis I
Context
Axis II
Acuity
Axis IV
Course
◽ General Population (screening/prevention)
◽ Mixed Clinical Setting (Treatment)
◽ Special Population
◽ Athlete _____
◽ Work _______
◽ Claim (Workers’ Compensation)
◽ Other _____________
◽ Acute (0-6 wk)
◽ Subacute (<3 mo)
◽ Chronic (>3 mo)
◽ Isolated episode
◽ Recurrent
◽ Persistent
◽ predictable
◽ unpredictable
Axis III
Pathology
◽ Tendinosis
◽ Paratenonitis
◽ Mixed
Axis V
Distribution
Axis VI^
Irritability
◽ Type 1: Unilateral signs/symptoms localized to lateral elbow
◽ Type 2: Bilateral signs/symptoms that are localized to lateral elbows
◽ Type 3 : Elbow + Cervical: Lateral elbow symptoms/signs combined with
cervical signs/symptoms or neuropathic pain
◽ Level 1: Mild pain* occurring after exercise/work,
lasts <6 hours
Mild
◽ Level II: Mild pain* occurring after exercise/work
that lasts 7-48 hours
◽ Level III: Mild pain* occurring during exercise/
work that persists after activity, but does not limit
activity
◽ Level IV: Mild* to moderate** pain that occurs
during exercise/work activity, persists >6 hours
and limits activity
Moderate
◽ Level V: Moderate** overall pain ratings; severe
pain with heavy activities of daily living
◽ Level VI: Moderate** to severe*** overall pain
ratings; severe pain with light activity; intermittent
pain at rest
Severe
◽ Level VII: Constant pain at rest, severe*** pain
with activity, pain disturbs sleep
Journal of Orthopaedic & Sports Physical Therapy®
Downloaded from www.jospt.org at on January 15, 2023. For personal use only. No other uses without permission.
Copyright © 2022 Journal of Orthopaedic & Sports Physical Therapy®. All rights reserved.
journal of orthopaedic & sports physical therapy | volume 52 | number 12 | december 2022 | cpg15
Lateral Elbow Pain and Muscle Function Impairments: Clinical Practice GuidelinesLateral Elbow Pain and Muscle Function Impairments: Clinical Practice Guidelines
CI: 0.88, 0.99).
52
Although US represents a less costly imag-
ing option than MRI, its diagnostic accuracy is ultimately de-
pendent on numerus variables such as operator experience,
equipment, and stage of pathology.
71
Nonimaging techniques
using electrodiagnostic studies, including electromyography
and nerve conduction studies, may also be used to rule out
compressive neuropathy involving the radial nerve as a cause
of lateral elbow pain.
Examination
OUTCOME, ACTIVITY LIMITATIONS,
SELF-REPORT MEASURES
Overview
Several outcome measures have been developed to assess
patients with LET. The PROMs that are most widely used
are the Patient Rated Tennis Elbow Evaluation (PRTEE), the
DASH questionnaire, the numeric pain-rating scale (NPRS),
and the Patient-Specific Functional Scale (PSFS) (
TABLES 9-12).
The commonly used clinician-based outcome measures are
the Mayo Elbow Performance Index (MEPI) and Roles and
Maudsley score (RM Score) (
TABLES 13-14).
ACTIVITY LIMITATIONS PHYSICAL
PERFORMANCE MEASURES
Activity limitation measures have not been reported in the lit-
erature, other than what is indicated for the patient self-report
questionnaires. The objective quantification of the following
activities can help the clinician to assess changes in the pa-
tient’s level of function over time: hand and arm use; turning
or twisting the hands or arms; lifting and carrying objects; fine
motor use of hand; throwing, bat, and racket activity in sport.
Clinicians can utilize easily reproducible activity limitation
and participation restriction measures associated with their
patients’ elbow pain to assess the changes in the patient’s
level of UE function over the episode of care.
Evidence Synthesis
Based on the results from high-quality clinical measurement
studies, the PRTEE, DASH, PSFS, and VAS all have demon-
strated excellent test-retest reliability, moderate to high levels
of construct validity, high levels of sensitivity to change, and
responsiveness in several populations. However, except for
the PRTEE, all the other self-report measures lack validation
in an LET population. Because the PSFS assesses restriction
of functional activities important to each individual, rigorous
activities that are not assessed in other self-report measures
(eg, work, hobbies, or athletic endeavors) can be monitored
objectively over time. Optional work and sports/performing
arts modules of the DASH may also provide valid, reliable,
and responsive measures of important functional tasks in-
volving the UE. The clinician-based outcome measures
(MEPI and RM Score) have demonstrated acceptable levels
of clinical measurement properties; however, there is a pau-
city of evidence in terms of the number of studies. Neither
the RM Score or the MEPI have been validated extensively
in a population of individuals with LET. Validated outcome
measure(s) should be administered at baseline and discharge
with other follow-up points being obtained as needed to as-
sess change for all patients with LET.
Gaps in Knowledge
More high-quality studies are required to evaluate the
clinical measurement properties, especially construct va-
lidity and responsiveness, including MCID of the DASH,
PSFS, and VAS in the LET population. The clinical mea-
surement properties of the RM Score and MEPI need to be
evaluated in the LET population to further support their
use and effectiveness in an LET population. Studies are
also needed to support the interpretation of objective and
reproducible measures of activity limitation and perfor-
mance measures.
RECOMMENDATION
A
Clinicians should use the diagnosis-specific PRTEE
to assess pain/irritability and function and/or the
region-specific DASH to assess UE function at
baseline and at least one other follow-up point, which in-
cludes discharge, for individuals with LET.
A
Clinicians should use the PSFS for patients with
high-demand activities and/or should administer a
scale that assesses activity-specific disability (eg,
DASH work or sports/performing arts module) at baseline
and at least one other follow-up point, which includes dis-
charge, for individuals with LET.
Journal of Orthopaedic & Sports Physical Therapy®
Downloaded from www.jospt.org at on January 15, 2023. For personal use only. No other uses without permission.
Copyright © 2022 Journal of Orthopaedic & Sports Physical Therapy®. All rights reserved.
Este documento contiene más páginas...
Descargar Completo
epicondilitis. jospt.2022.pdf
 Estamos procesando este archivo...
 Lamentablemente la previsualización de este archivo no está disponible. De todas maneras puedes descargarlo y ver si te es útil.
Descargar
Estamos procesando este archivo...
Lamentablemente la previsualización de este archivo no está disponible. De todas maneras puedes descargarlo y ver si te es útil.